
Psoriasis
Psoriasis is an inflammatory skin condition that affects roughly 2% of the UK population, and it can look different depending on your skin tone, appearing pink or red on lighter skin, and grey, violet or darker brown on darker skin. There are different types of psoriasis, and symptoms can range from mild to severe, so the experience varies from person to person. Psoriasis is also more than a skin condition: it’s linked to a higher risk of other conditions, including psoriatic arthritis, diabetes, heart disease, Crohn’s disease, obesity, anxiety and depression, which is why understanding it fully matters as much as managing the visible symptoms. Here we take a deep dive into the condition and explore everything from symptoms and appearance to triggers and treatment.
Table of Contents
- What is psoriasis?
- Types of Psoriasis
- What Does Psoriasis Look Like?
- Psoriasis on Dark and Brown Skin Tones
- Where Does Psoriasis Appear on the Body?
- General symptoms of psoriasis
- Psoriasis triggers and factors
- Psoriasis and Inflammation
- Psoriasis, Gut Health and Crohn’s Disease
- Scratching Psoriasis: Why You Should Avoid It and What to Do Instead
- Managing and Treating Psoriasis
- Conclusion
- Psoriasis FAQ
What is psoriasis?
Psoriasis is a common, long-term skin condition that is thought to be related to immune system over-activity (Source). People with psoriasis have an increased production of skin cells: whereas skin cells are normally created and replaced every 3-4 weeks, for those experiencing psoriasis, the process only takes about three to seven days. As a result, sufferers experience a build-up of skin cells, creating dry, scaly patches of skin.
Psoriasis can happen at any age, but most often starts between the ages of 10 and 35. Although there is no cure for psoriasis, you might find you go through periods of time when symptoms are better and other times when your psoriasis flares-up. As a first step to managing the condition, it’s helpful to understand the different types of psoriasis and the triggers commonly associated with flare-ups.
Psoriasis can also affect more than the skin – you might find it has an impact on your nails or joints too. It may also be associated with other medical conditions such as diabetes, heart disease, Crohn’s disease, obesity, anxiety and depression.
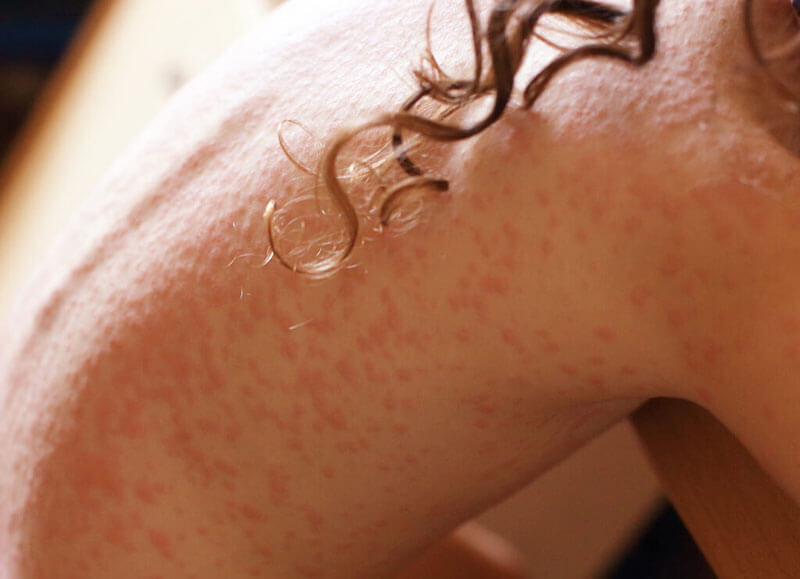
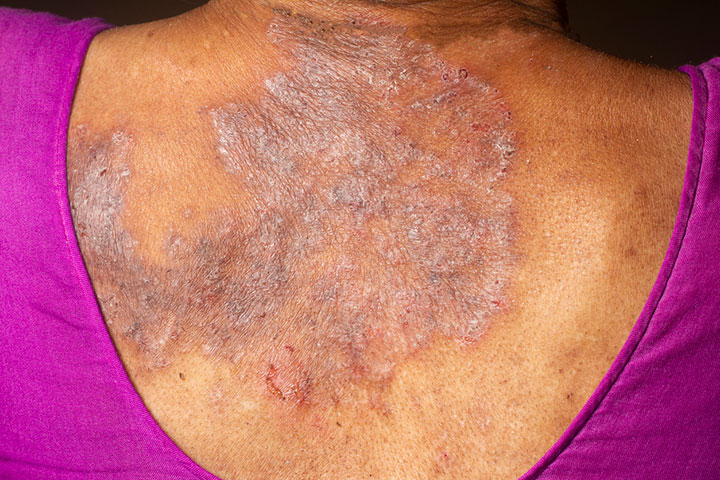
Types of psoriasis
There are a number of different types of psoriasis (source), but the following are the most common.
Plaque Psoriasis
Plaque psoriasis is by far the most common type of psoriasis, affecting 9 out of 10 sufferers. It is also known as psoriasis vulgaris. Normal skin cells are replaced every 3-4 weeks but in psoriasis this happens every 3-4 days. This is thought to be due to genetics and environmental factors.
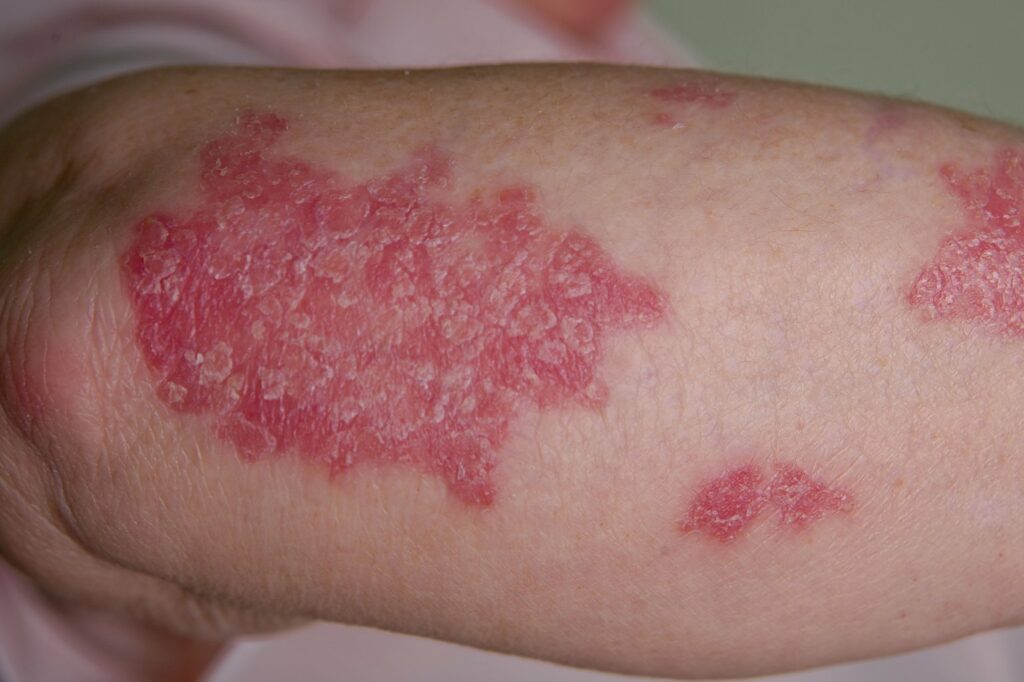
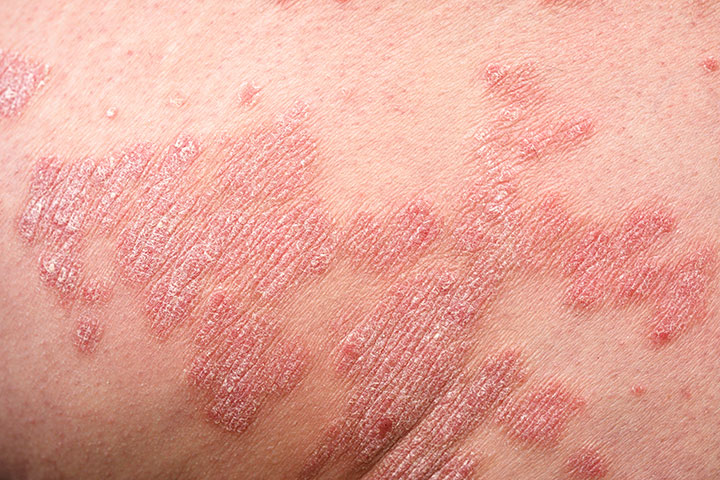
Plaque psoriasis appears as well-defined patches of irregularly shaped, or oval, pink-red skin covered in silver-white scales (referred to as ‘plaques’). The thickness of the scales can vary. On darker skin, plaques may appear grey, violet or dark brown rather than pink-red, and the silvery scale can be harder to see against the skin’s natural tone. See Psoriasis on Dark and Brown Skin Tones below for more detail. The plaques are most often on the forearms, shins, knees, elbows, scalp, behind the ears, on the torso and around the buttocks. The skin may be itchy, but not usually sore, and can also crack – especially if the palm of the hands or soles of the feet are affected.
While it is a long-term condition, around 1 in 4 people with plaque psoriasis can find it goes away for months at a time.
Erythrodermic psoriasis
Erythrodermic psoriasis is a rare, potentially life-threatening type of psoriasis. It is thought be caused by genetics and some environmental factors. Erythrodermic psoriasis can develop gradually or come on suddenly – spreading across the whole body to affect more than 90% of the skin. You might also feel unwell with fatigue, fever and develop swollen lower legs. If you have these symptoms you should go straight to A&E.
Erythrodermic psoriasis can happen in anyone with plaque psoriasis but can be triggered by factors like infections or skin irritants.
Flexural psoriasis
Flexural psoriasis, also known as inverse psoriasis, affects the creases and folds of your skin. It can cause itchy, red, glazed areas in your skin folds, such as the armpits, groin, genitals, buttocks and under the breasts. Sweat or rubbing the affected skin can cause further irritation. The condition is more common in people who are overweight, immobile or elderly. You may also find you’re more prone to developing yeast infections in the same areas as your flexural psoriasis.
Guttate Psoriasis
This form of psoriasis is also known as ‘raindrop’ or ‘droplet’ psoriasis because it looks like droplets on the skin. Certain people who have had guttate psoriasis will develop chronic plaque psoriasis later in their life. Guttate Psoriasis most frequently occurs in children and teenagers, usually after a throat infection caused by streptococcal bacteria. Even though it may be caused by an infection, guttate psoriasis is not contagious. The condition develops over the course of a week, with many small, raised, scaly patches that are round or oval and pink or red appearing all over the body. For more information on guttate psoriasis, visit our dedicated Guttate Psoriasis page.
Nail psoriasis
Nail psoriasis affects the fingernails and toenails with a range of symptoms. Nails may turn orange-yellow, become pitted, start to come away from your skin or disintegrate. The condition is more likely to affect your fingernails than your toenails. Nail psoriasis can happen in anyone with psoriasis, but it is particularly common if you also have arthritis-associated psoriasis.
Pustular Psoriasis
This is a rare type of psoriasis where there are pus-filled spots on or surrounded by red skin. There are two main types of pustular psoriasis: generalised and localised. Around 5% of people with psoriasis experience localised pustular psoriasis, but in rare cases this can be generalised which can be life threatening. Localised pustular psoriasis (also known as palmoplantar psoriasis) appears as yellow-brown blisters, known as ‘pustules’, on your palms and soles along with scaly skin and redness on your toes and fingertips. In generalised pustular psoriasis, redness spreads quickly over your skin followed by the development of multiple white pustules that group together to form large areas of pus. These blisters are not contagious.
Pustular psoriasis is more common in those who have, or have had, plaque psoriasis. However, you can develop it even if you’ve never had psoriasis before. Triggers range from stress, certain medicines and infections to pregnancy or too much sun. Localised pustular psoriasis usually occurs in those aged 20-60, particularly if you smoke.
Scalp Psoriasis
Scalp psoriasis looks like plaque psoriasis, but affects your scalp. Your hair traps the scale making it hard to rub away, and as a result the plaques can become thick. Some people find that only parts of their scalp is affected, while for others it’s across their whole scalp. In some cases scalp psoriasis can even cause bald patches, but the hair will normally grow back. Up to 9 out of 10 people with psoriasis develop it on their scalp. Some people may experience itchy scalp, a feeling of tight skin and occasionally soreness if the skin cracks.
A gentle, medicated scalp routine can help manage symptoms alongside any prescribed treatment, see E45 Dry Scalp Serum and E45 Dry Scalp Shampoo. For more information on scalp psoriasis, visit our dedicated Scalp Psoriasis page.

Since psoriasis can appear in so many forms, ranging from common scaly plaques on elbows to smooth red patches in skin folds, recognising the specific signs is useful for getting the right care. If you notice widespread redness or feel unwell alongside skin symptoms, seeking professional advice is necessary to ensure your safety.
What Does Psoriasis Look Like? Symptoms and Appearance
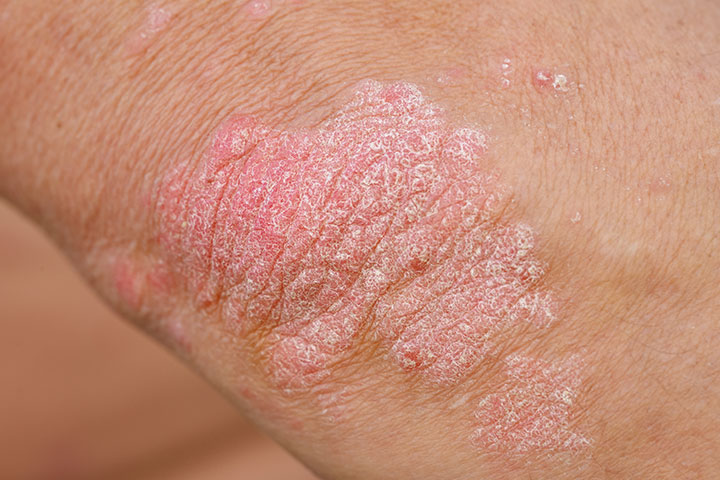
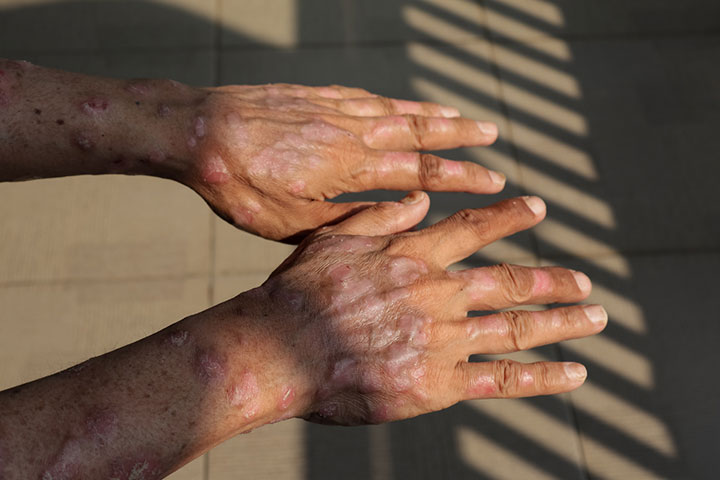
What does psoriasis look like? Psoriasis typically appears as raised, inflamed patches of skin called plaques, often covered with a build-up of silvery-white scale. These patches can be small and localised or spread across larger areas of the body, and they commonly feel itchy, sore, or tight, especially where the skin cracks.
As the skin cells that make up a plaque are replaced far faster than normal, the surface can flake and peel, sometimes shedding visible flakes onto clothing. In more active or inflamed areas, the skin may feel warm, and scratching or picking at plaques can cause them to bleed.
How psoriasis looks can vary significantly depending on your skin tone. On lighter skin, plaques usually appear pink or red with silvery scale. On darker and brown skin, the same plaques often appear grey, violet or dark brown, and the scale can be harder to spot against the skin’s natural colour, so redness alone isn’t a reliable sign to look for.

Psoriasis on Dark and Brown Skin Tones
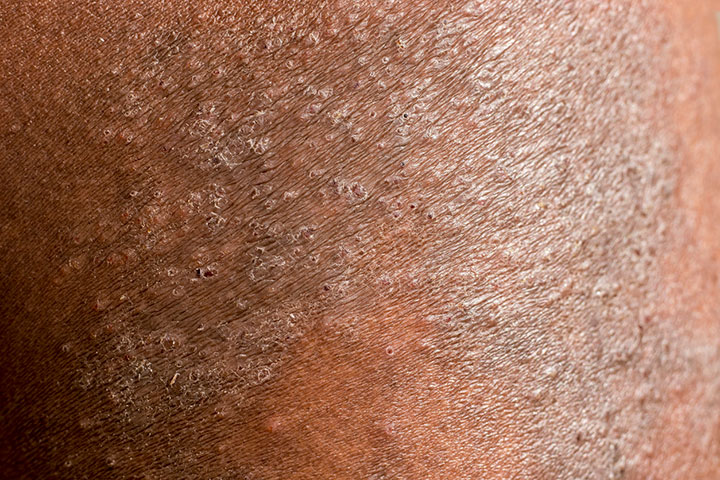
Psoriasis affects people of every skin tone, but it doesn’t always look the way it’s most commonly pictured. On darker and brown skin, plaques often present as grey, violet or dark brown, rather than the pink or red seen on lighter skin, and the silvery scale that’s easy to spot on lighter skin can be far less visible against a darker base tone. (Source)
After a flare settles, the affected area can be left with hyperpigmentation (darker patches) or, less commonly, hypopigmentation (lighter patches), which may take months to fade even once the psoriasis itself is under control.
Because clinical training and imagery has historically focused on how skin conditions present on lighter skin, psoriasis on darker skin tones is sometimes diagnosed later, or initially mistaken for another condition. (Source) If you notice persistent discolouration, scaling or thickened skin that doesn’t resolve, it’s worth seeing a GP or dermatologist for an assessment, regardless of whether the patch looks red.
Where Does Psoriasis Appear on the Body?
Psoriasis can appear anywhere on the body, but certain locations are especially common, and where it appears can affect both how it looks and how it’s best treated.
Back of the neck: plaque psoriasis often develops here, and hair products, collars and friction from clothing can aggravate it further.
Stomach and torso: plaques on the trunk are common in both plaque and guttate psoriasis, and can spread across a wide area during a flare.
Feet and palms: palmoplantar psoriasis specifically affects the soles of the feet and the palms of the hands. It can cause the skin to thicken and crack, and painful fissures can develop that make walking or using your hands genuinely uncomfortable. (Source)
Skin folds: psoriasis in the armpits, groin and other skin folds is known as flexural (or inverse) psoriasis, covered in more detail in Types of Psoriasis above.
Scalp: also covered above, but worth noting scalp involvement is extremely common, affecting up to 9 in 10 people with psoriasis.
Wherever it appears, psoriasis is the same underlying condition, but location genuinely matters for treatment. Thicker-skinned areas like the palms and soles often need stronger treatment to penetrate the skin, while delicate areas like skin folds need gentler options to avoid irritation. If you’re not sure what’s right for where your psoriasis is affecting you, it’s worth discussing this with your GP or dermatologist.
General symptoms of psoriasis
Although there are many different types of psoriasis with different symptoms, most people have plaque psoriasis. Around 80% of those with psoriasis have a mild form where just a few areas of skin are affected and can be easily managed. You may experience some, or all, of the following psoriasis symptoms, depending on severity and type:
- Dryness
- Cracked skin
- Blisters/ pustules
- Red skin
- Bleeding skin
- Itchy skin
- Sore painful skin
- Skin build-up / Silver scaly skin
- Glazed skin
Psoriasis triggers and factors
While psoriasis often has a genetic component, several other factors can contribute to its development or trigger flare-ups. Below are some of the most common triggers that may bring on psoriasis or worsen existing symptoms.
Medications
Medicines that can cause or trigger psoriasis include:
- Lithium
- Anti-malarial drugs
- Some blood pressure drugs, such as beta-blockers and ACE inhibitors
- Coming off steroids too quickly, like prednisone
- Some antibiotics, like penicillin and tetracycline
- Non-steroidal anti-inflammatory drugs
- Some anti-depressants, like trazodone
Stopping steroid medicines suddenly can trigger pustular or erythrodermic psoriasis.
Injury
Damage to the skin from scratches, burns, insect bites, piercings, tattoos or sunburn can trigger psoriasis. Also known as the ‘Koebner phenomenon’, this happens in about 25% of people with psoriasis – with symptoms developing about 1-2 weeks after the skin is damaged.
Lifestyle
Smoking and excessive or frequent drinking can make your psoriasis flare up. Localised pustular psoriasis usually only develops in smokers. Those who drink too much may find this makes their psoriasis treatment less effective. Maintaining a healthy weight can also help. Excess body fat increases inflammation in the body and can make psoriasis more difficult to manage. Adopting healthy eating habits, staying active, and – when needed – seeking professional support for weight reduction can significantly improve skin symptoms and overall wellbeing.
Stress
Stress is a common psoriasis trigger.
Weather and sunlight
Both cold, dry weather and excessive sun exposure can trigger psoriasis flare-ups in some people. However, moderate sunlight often helps improve symptoms. Controlled light treatment (phototherapy) under medical supervision can be an effective and safe option. It’s important to avoid sunburn and overexposure, as these can worsen psoriasis, accelerate skin ageing, and increase the risk of skin cancer.
Identifying what sets off your skin is a helpful step in managing psoriasis, whether that be stress, certain medications, or lifestyle habits like smoking. Being aware of these factors is key to helping you stay in control of your flare-ups.
Psoriasis and Inflammation
Is psoriasis an inflammatory condition? Yes, psoriasis is fundamentally driven by inflammation. It develops when the immune system becomes overactive and mistakenly speeds up the skin’s natural renewal process: skin cells that would normally take three to four weeks to form and shed are instead replaced every three to seven days. This rapid turnover causes cells to build up faster than they can be shed, creating the thickened, scaly plaques that are characteristic of psoriasis.
This inflammation isn’t limited to the skin. Because psoriasis is a systemic inflammatory condition, a growing body of research shows a higher risk of other inflammatory conditions, including psoriatic arthritis, cardiovascular disease, and inflammatory bowel disease. (Source) This is one reason why managing psoriasis is about more than the visible symptoms alone.
Psoriasis, Gut Health and Crohn’s Disease
Is psoriasis connected to gut health? There’s a growing body of evidence linking the two. Psoriasis and Crohn’s disease are both immune-mediated inflammatory conditions, and people with psoriasis have a higher likelihood of also developing inflammatory bowel disease (IBD), which includes Crohn’s disease and ulcerative colitis. (Source)
Researchers believe the gut microbiome, the community of bacteria living in your digestive system, may play a role in how severe psoriasis symptoms are, though this is still an active area of research rather than settled science. Diet doesn’t cause or cure psoriasis, but a generally healthy, balanced diet rich in fruit, vegetables and whole grains supports overall wellbeing alongside your treatment. (Source)
If you have psoriasis and are also experiencing digestive symptoms, such as ongoing stomach pain, diarrhoea, or blood in your stool, it’s worth raising this with your GP or dermatologist, rather than assuming the two are unrelated conditions.
Scratching Psoriasis: Why You Should Avoid It and What to Do Instead
It’s natural to want to scratch an itchy psoriasis plaque, but scratching tends to make things worse rather than better. It can trigger new plaques to form at the site of the scratch, through what’s known as the Koebner phenomenon (see Triggers and Factors above), so scratching can genuinely spread your psoriasis rather than just relieve it. Scratching can also break the skin, leading to bleeding, infection, or scarring, and any relief it brings is usually short-lived, making the itch-scratch cycle harder to break. (Source)
Instead, try cooling the area with a cold compress, applying your emollient rather than scratching, and keeping nails short to limit damage if you do scratch without thinking. If itching is severe, disrupting your sleep, or not responding to your usual routine, E45 Itch Relief products can help, and it’s worth speaking to your GP if it remains unmanaged.
Managing and Treating Psoriasis
Psoriasis can’t be permanently stopped or cured, but it can be effectively managed. The most reliable approach combines avoiding your personal triggers, using a daily emollient to support your skin barrier, and following an appropriate treatment plan for your type and severity of psoriasis, whether that’s topical, light-based or systemic treatment. For most people, a combination of these approaches, rather than relying on any single fix, brings the best long-term control over flare-ups and day-to-day symptoms.
Avoiding certain triggers
The following precautions can help to reduce your psoriasis symptoms if you find that certain triggers exacerbate your symptoms:
- Speak to your doctor or pharmacist about whether you should be starting or stopping any medicines that could be affecting your psoriasis.
- Treat any skin injuries quickly: To avoid insect bites, cover up and use insect repellent or stay indoors at dawn and dusk when insects are most active. Try to avoid cuts when shaving by putting a moisturiser under your shaving cream.
- Wear sunscreen to avoid sun damage; ideally one that is a broad-spectrum sunscreen with SPF 30 or higher, and water resistant. Read more in our sunscreen guide and SPF and sun protection guide.
- Avoid smoking and limit alcohol intake – both can worsen inflammation and make psoriasis flare-ups more frequent or severe.
- Reduce stress with healthy sleep habits, regular exercise and relaxation techniques, such as deep breathing, yoga, tai chi or meditation. Maintaining a balanced diet and adequate hydration also supports overall skin health and may help reduce inflammation.
- Protect your skin from extreme cold by wearing winter clothing, including hats and gloves. Don’t sit close to radiators or fires.
- In warmer months, use a humidifier to put moisture back into the air and avoid air conditioning.
- Apply a moisturiser throughout the day when your skin feels dry. Learn more about how to keep your skin hydrated and view our hydrating skincare products.
- Limit showers and baths to 10 minutes; use warm water rather than hot water.
Psoriasis treatments
When it comes to treating your psoriasis, it’s best to consult with a healthcare professional who can advise on the best treatment plan for you tailored to your psoriasis type and symptoms. Below, we’ve listed a few common treatment methods.
Emollients
Emollients are moisturisers that can help reduce the scaling and itching caused by psoriasis. Not only can they make your skin look better by removing scales, they can also make it easier to apply other psoriasis treatments – even helping them to penetrate deeper into your skin.
Applying an emollient like E45 Psoriasis Cream every day can help to manage your psoriasis by:
- Helping to reduce symptoms such as scaling, itching, redness, roughness and hardening of the skin
- Replacing lost water in the skin
- Helping to stabilise the skin barrier and protect the skin from damaging irritants and allergens
- Helping to reduce inflammation and normalise skin cell production
As regular soaps and cleansers can irritate the skin and cause dryness, it’s important to wash with an emollient too. There are special emollients that can be used for washing just as you would use soap, such as E45 Emollient Shower Cream, or you can apply your leave-on emollient as a soap substitute. You can also add emollients to your bath, such as E45 Emollient Bath Oil.
Topical treatments
Topical therapies are the first-line treatment for most people with psoriasis. They help reduce inflammation, itching, and scaling directly on the affected skin. Common options include:
- Corticosteroids – help to calm inflammation and redness. Always use these under medical supervision, as your doctor will prescribe the right strength and duration for your condition.
- Vitamin D analogues (such as calcipotriol or calcitriol) – regulate skin cell growth and can be used alone or combined with topical steroids.
- Combination treatments – some creams or ointments combine corticosteroids with salicylic acid (to remove scale) or calcipotriol (to enhance effect).
- Calcineurin inhibitors (tacrolimus or pimecrolimus) – used particularly on delicate areas such as the face, genitals, or skin folds, where steroids may not be suitable.
- Coal tar or dithranol – these are older, but effective treatments that can help to reduce thick scaling.
When using topical treatments, continue applying your emollients regularly. Apply your emollient first, then your prescribed cream or ointment about 20–30 minutes later to improve absorption and tolerance.
Systemic therapies
If topical treatments and phototherapy are not sufficient, your dermatologist may recommend systemic (whole-body) therapies – taken as tablets, injections, or infusions. These treatments act from within to calm inflammation throughout the body and improve skin symptoms.
Common options include:
- Methotrexate, ciclosporin, or acitretin – long-established medicines that can effectively control moderate to severe psoriasis (conventional therapy).
- Biologic agents – targeted injections or infusions that block specific immune pathways, such as TNF-α, IL-17, IL-23, or IL-12/23.
- Small-molecule drugs – such as apremilast or deucravacitinib, which modulate inflammation in a more targeted way.
Because systemic treatments can affect other organs, they require regular medical monitoring and careful selection based on your overall health, disease severity, and treatment goals.
Even while on systemic therapy, it is important to maintain good skin care – including daily use of emollients and moisturisers – to support the skin barrier and enhance comfort.
Your dermatologist will tailor your treatment plan to your individual needs and closely monitor your progress.
Taking a proactive approach to your skin involves avoiding common triggers like stress or injury and keeping up with a regular moisturising routine. It is also a good idea to work with a healthcare professional to find the right balance of treatments, whether that includes emollients or prescribed medicines.
Conclusion
Psoriasis is a skin condition that occurs as a result of an immune system reaction. Whilst there is no cure for psoriasis, many sufferers find they can go through periods of time when symptoms are better, and other times when they experience more aggressive flare-ups. As a first step to managing the condition, it’s helpful to understand the different types of psoriasis and the triggers commonly associated with flare-ups. It’s also important to consult with a healthcare professional for a tailored treatment plan.
Psoriasis FAQs
What causes psoriasis?
Psoriasis is thought to be related to immune system over-activity. People with psoriasis have an increased production of skin cells: whereas skin cells are normally created and replaced every 3-4 weeks, for those experiencing psoriasis, the process only takes about three to seven days. As a result, sufferers experience a build-up of skin cells, creating dry, scaly patches of skin. There are many things that can trigger or exacerbate psoriasis symptoms and understanding these triggers can be helpful when it comes to managing the skin condition.
What is psoriasis?
Psoriasis is an inflammatory skin condition that affects roughly 2% of the UK population. There are different types of psoriasis and the symptoms can range from mild to severe, so it can vary from person to person.
How to cure psoriasis permanently
Although there is no cure for psoriasis, you might find you go through periods of time when symptoms are better and other times when your psoriasis flares-up. As a first step to managing the condition, it’s helpful to understand the different types of psoriasis and the triggers commonly associated with flare-ups.
What is the best treatment for psoriasis?
There are many precautions that you can take to better manage your psoriasis – from understanding and avoiding certain triggers to using emollients. This also includes consulting with a healthcare professional who can give you tailored advice on certain treatment options that might be right for you.
What are the signs of psoriasis?
You may experience some, or all, of the following psoriasis symptoms, depending on severity and type:
- Dryness
- Cracked skin
- Blisters/ pustules
- Red skin
- Bleeding skin
- Itchy skin
- Sore painful skin
- Skin build-up / Silver scaly skin
- Glazed skin
Can stress cause psoriasis?
For some, stress can be something that triggers or exacerbates psoriasis symptoms. It might be helpful to try reducing stress with healthy sleep habits, regular exercise and relaxation techniques, such as deep breathing, yoga, tai chi or meditation.
Can psoriasis go away?
Psoriasis is a lifelong, chronic condition, which means there is no psoriasis cure. It can go away from time to time, though, as it often works in cycles. Plus, finding the right treatment can help you manage symptoms when flare-ups occur.
What’s the best treatment for psoriasis?
There are plenty of medications, therapies, and creams for psoriasis. Different treatments work differently for everyone. Speak to a dermatologist if you need treatment for severe psoriasis. If you need something to help minimise drying and itching, the Decubal anti-itch gel works great.
Is psoriasis genetic?
Researchers have found a link between psoriasis and genetics. A child is more likely to develop psoriasis if their parent has the condition.
Can you have both eczema and psoriasis?
Yes – it is possible for a person to have psoriasis and eczema together. Each condition requires its own treatment.
Does psoriasis increase the likelihood of getting arthritis?
A study has found that adults with psoriasis are more likely to get rheumatoid arthritis than those without. It’s important to note that having psoriasis can put you at a higher risk of other conditions, such as obesity, type 2 diabetes, arthritis, and mental health conditions.
Is psoriasis contagious?
No – psoriasis is not contagious. No one can spread psoriasis to another person.
What does psoriasis look like on dark or brown skin?
On darker skin tones, psoriasis patches often appear grey, violet or dark brown rather than red or pink, and the scale on top may be less visible against the skin’s natural tone. The condition can still cause significant discomfort, itching and thickened skin, so it’s worth getting any persistent patches checked even without redness.
Is psoriasis connected to gut health?
There’s a recognised link: people with psoriasis have a higher risk of also developing inflammatory bowel disease, such as Crohn’s disease, and gut health is thought to play a role in how severe psoriasis symptoms can be. If you notice digestive symptoms alongside your psoriasis, it’s worth mentioning this to your GP.
Should I scratch psoriasis?
No, scratching psoriasis isn’t recommended, as it can worsen the condition, break the skin, and even trigger new plaques to form at the site of the scratch, through what’s known as the Koebner phenomenon. Cooling the area or applying emollient are better alternatives when the itch is hard to ignore.
Where does psoriasis most commonly appear on the body?
Psoriasis most commonly appears on the knees, elbows, scalp, lower back, neck, stomach and feet, though it can develop anywhere on the body. Where it appears can affect both how it looks and which treatment works best.
















































